
When the Lower Anterior Teeth Leave No Room for Upper Restorations, What Should We Do?
Suppose we want to restore the maxillary anterior teeth, but the mandibular anterior teeth leave too little space. Can we solve the problem by shortening the lower incisal edges?
Sometimes yes; but before reducing anything we need to identify why the space is lacking. Have the lower teeth over-erupted, or does the problem lie in the jaw relationship and the loss of posterior support?
A review article and a case report show two different situations that matter in clinical decision-making.
First, Find the Cause of the Lack of Space
If the incisal edges of the mandibular anterior teeth sit too far coronally relative to the reference occlusal plane, we should think of supraeruption.
But in worn teeth, crown length alone should not be the criterion. Sometimes the tooth has gradually moved coronally together with the gingival tissue; a phenomenon called compensatory eruption.
In this situation, shortening the incisal edge alone does not correct the unfavorable position of the tooth and the gingiva.
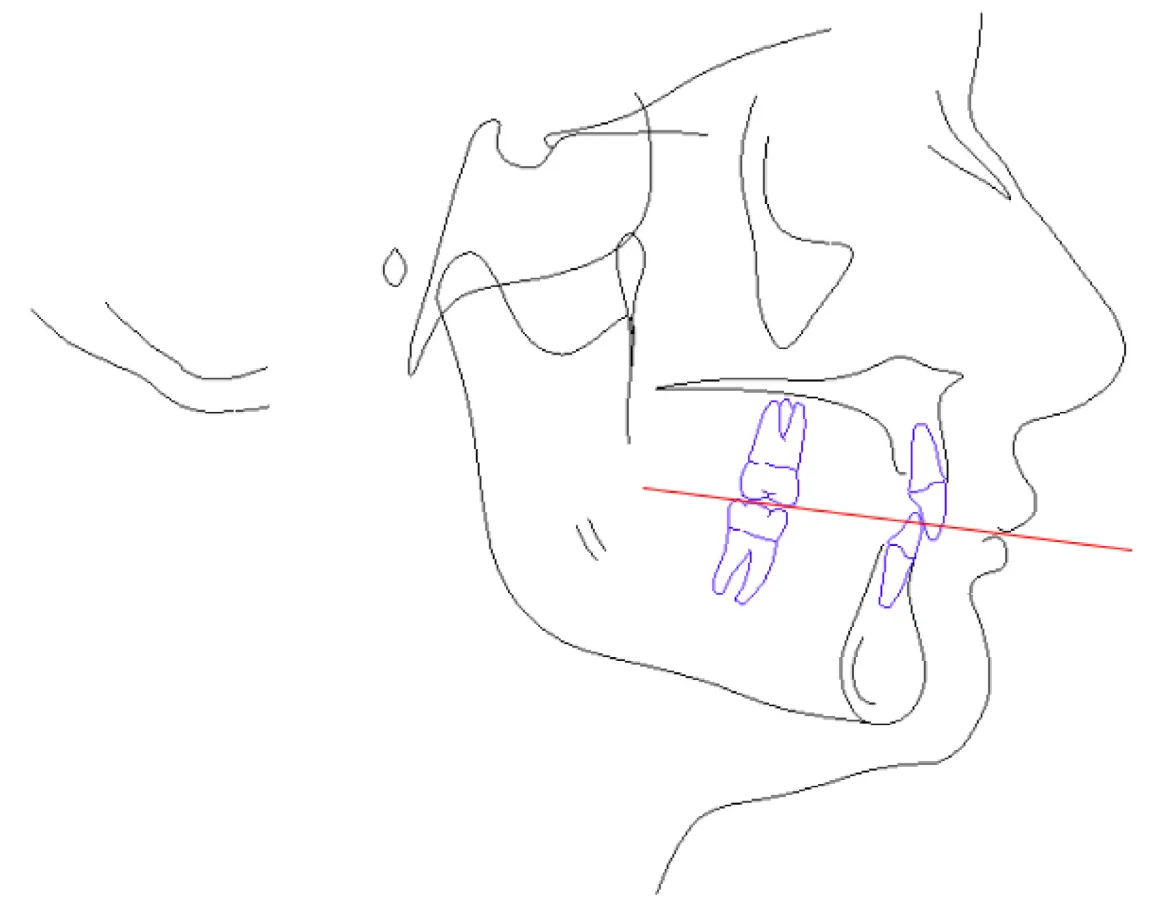
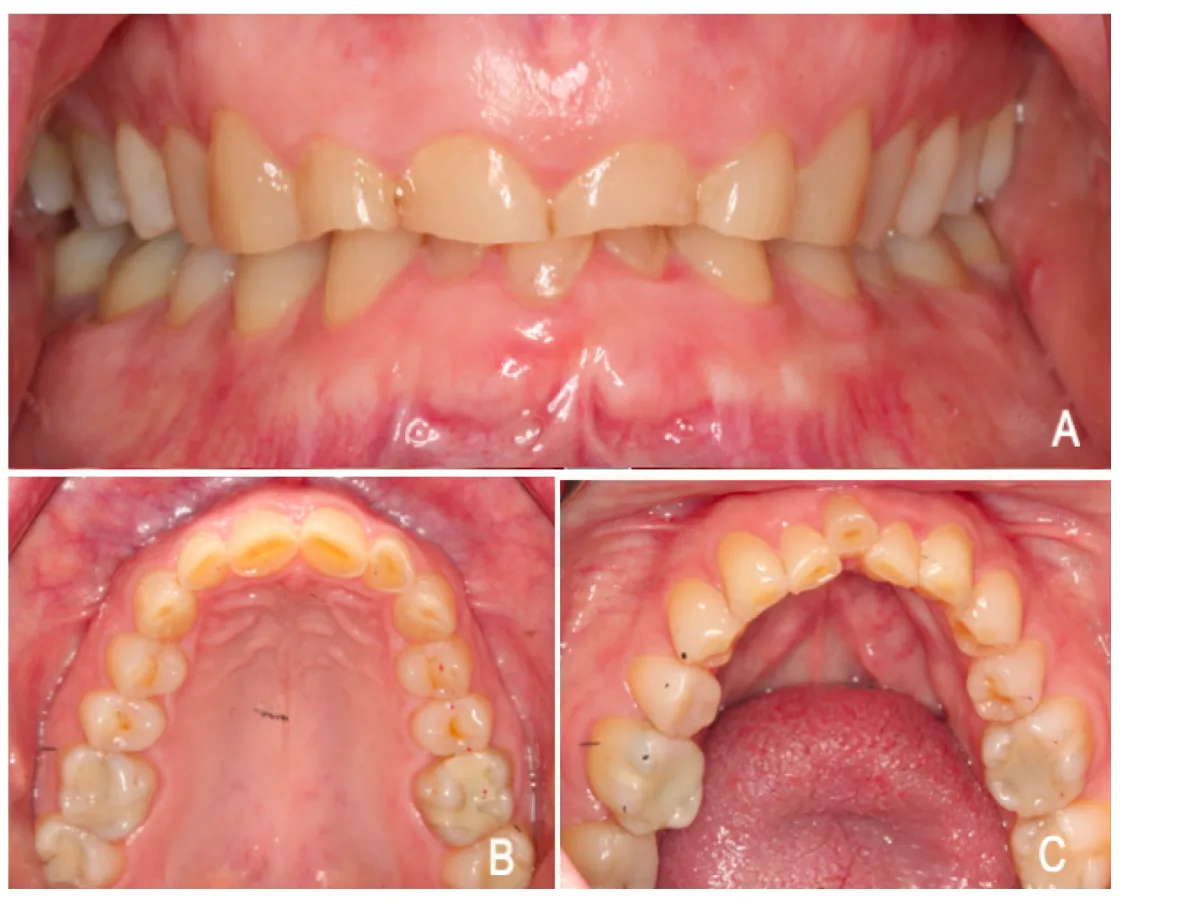
In a Clinical Case, Why Were the Lower Anterior Teeth Shortened?
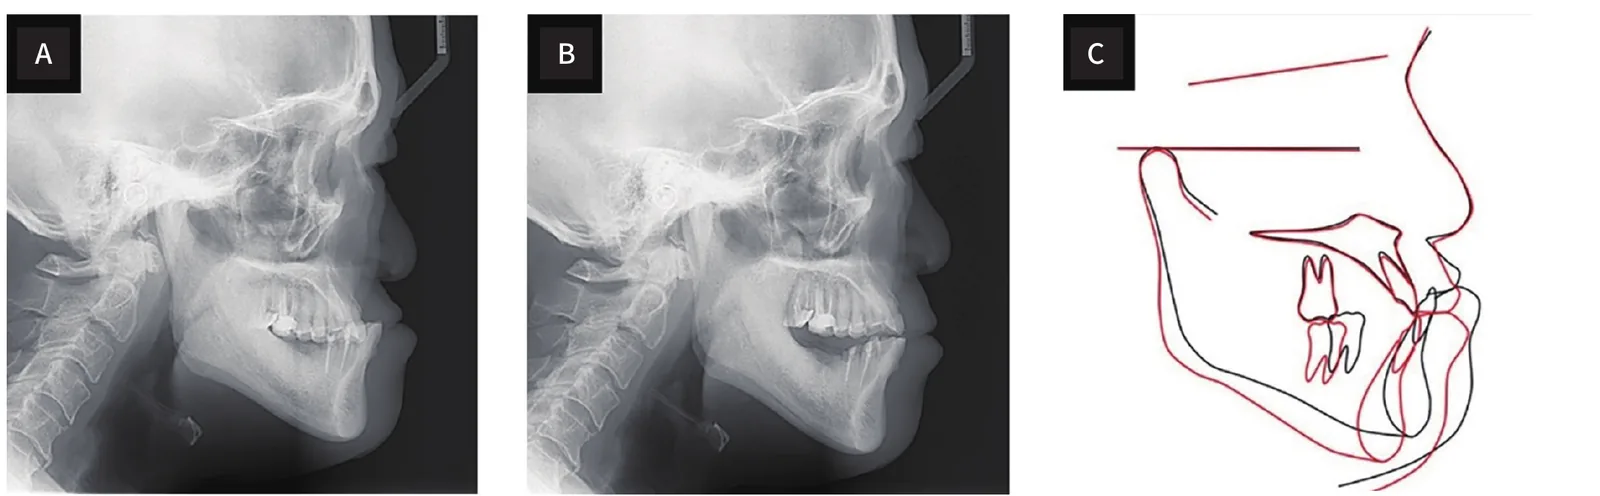
In the case report by Koo et al., the patient had a skeletal Class III relationship, severe tooth wear, a reduced OVD and loss of posterior support.
The clinicians first tested the new vertical dimension with a provisional overlay denture and evaluated the patient over several months.
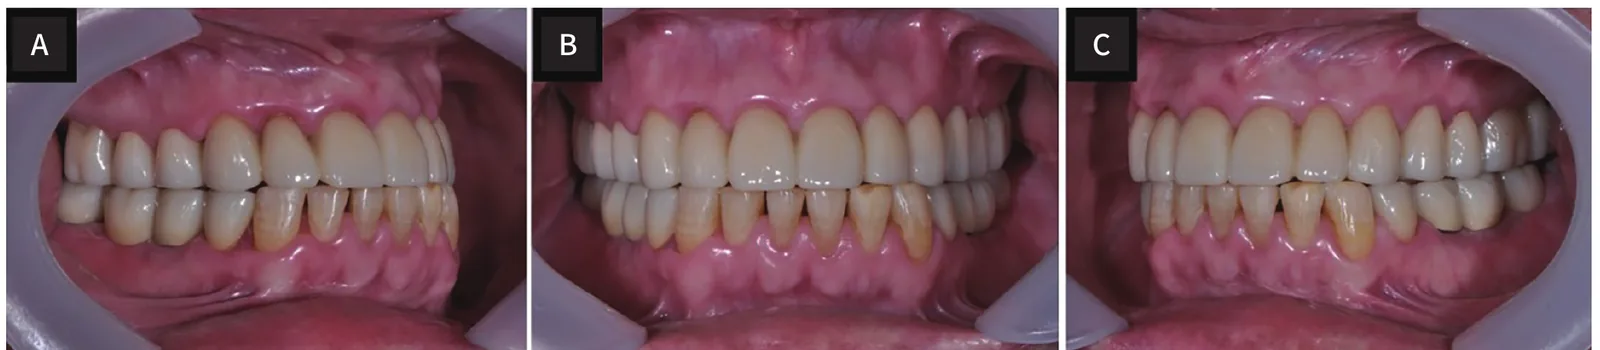
After the jaw relationship was changed, a number of the mandibular teeth interfered with the maxillary anterior teeth along the closing path. The incisal edges of these teeth were therefore selectively adjusted to provide the space needed for the anterior reconstruction.
The important point is that the incisal adjustment was not done at the outset; first the OVD and the jaw relationship were changed, and after evaluation the remaining interference was removed.
On the other hand, these teeth were not supraerupted, and because of wear they were even shorter than normal. Their reduction was therefore not a treatment for over-eruption, but a way of removing an interference that had arisen in the new jaw relationship.
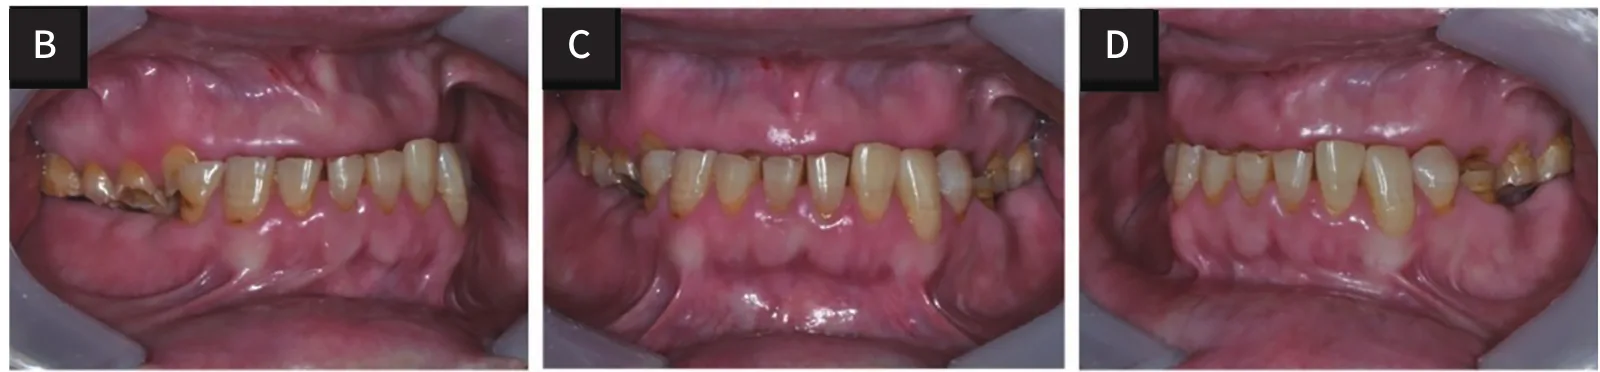
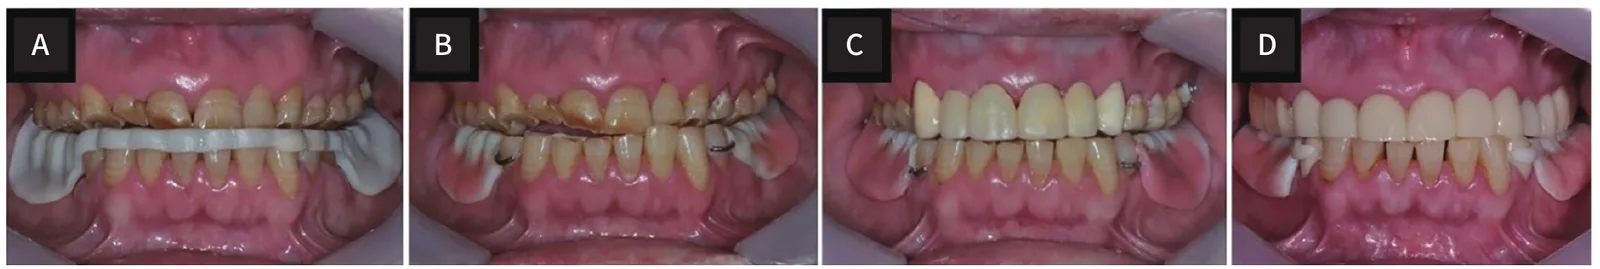
Why Did the Crossbite Improve?
The improvement in the anterior relationship came mainly from restoring the OVD and the backward and downward rotation of the mandible, not from shortening the teeth.
In the end, the anterior relationship went from a severe crossbite to edge to edge.
This result was a compromise treatment. Orthodontics or orthognathic surgery would have been needed to achieve normal overjet and overbite; but given the patient's circumstances and his satisfaction with the result, no further treatment was done.
When Is Orthodontics the Better Choice?
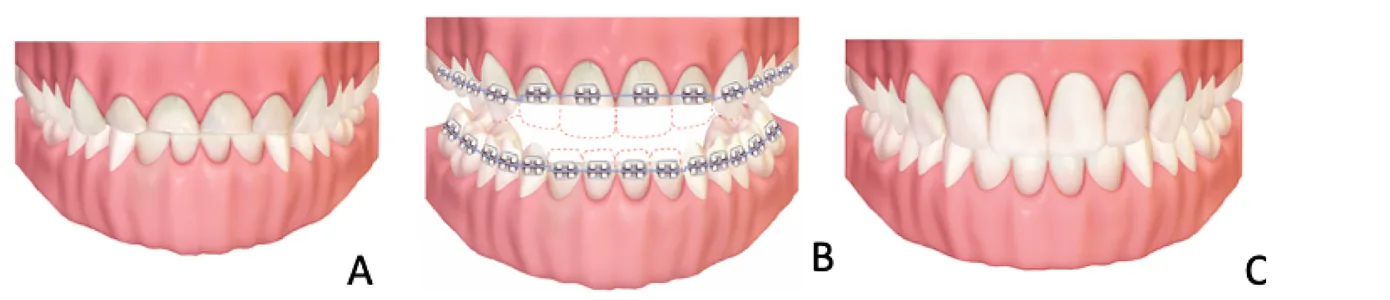
If the anterior teeth have undergone compensatory eruption together with the bone and gingiva, orthodontic intrusion can correct the position of the teeth and the gingival margin and reduce the need for incisal reduction.
This approach does take time, needs patient cooperation and a stabilization period, and the possibility of apical root resorption must also be considered.
In other situations, reconstruction of the posterior teeth with an increase in OVD, surgical crown lengthening or the Dahl concept may come into consideration. The choice of approach depends on the underlying cause of the lack of space and the overall treatment plan.
What Should We Check Chairside Before Deciding?
Before shortening the mandibular anterior teeth, check three things:
- Posterior support and OVD: are the patient's vertical dimension and jaw relationship appropriate?
- Tooth position: have the mandibular anterior teeth over-erupted relative to the reference occlusal plane?
- Wear and gingiva: has the wear been accompanied by compensatory eruption and a change in the position of the gingival margin?
If, after an appropriate OVD and jaw relationship have been established, only a local interference remains, selective incisal adjustment can be part of the treatment plan.
But if the problem stems from compensatory eruption or the loss of posterior support, shortening the tooth alone does not remove the underlying cause.
Limits of the evidence: this case report is one example of selective incisal adjustment after a change in the jaw relationship; it is not a reason to regard this approach as a routine replacement for orthodontics.